Abstract
Spinal degeneration consists of a cluster of disorders that affect the spine’s structural and functional purposes, some symptoms may include pain, reduced mobility, neurological impairment, and a disimproved way of life. An early diagnosis can be challenging as conventional methods detect changes within the spine after deterioration. This literature review has examined evidence surrounding the role of clinical symptoms, mechanical risk factors, imaging methods, and biomarkers in the early detection of spinal degeneration. Relevant studies that were already peer-reviewed have been identified through database searches, keeping needed, factual information in close accordance with the focus of this literature review. The findings of this literature review show that early clinical symptoms, consisting of neck pain, reduced dexterity, and motor impairment, may indicate initial progressions of disease onset but lack sufficient precision for a proper, reliable diagnosis. Mechanical factors like repetitive loading and progressive spinal stress were known to demonstrate a correlation with increased degenerative changes. Imaging techniques, specifically magnetic resonance imaging (MRI), showed strong results but detected abnormalities post-disease progression. Biomarkers, consisting of neurofilament light chain (NfL), glial fibrillary acidic protein (GFAP), and neural cell adhesion molecule (NCAM), have shown promise in identifying neuronal injury and level of severity of disease. However, there are challenges regarding clinical testing and disease specificity. From a basis, evidence suggests that a multimodal approach that integrates clinical assessment, risk-factor correlation, imaging techniques, and biomarker analysis has potential to improve early detection, but a bigger substantiate reach is required to confirm within at-risk populations.
Keywords: Spinal degeneration; Degenerative cervical myelopathy; Degenerative disc disease; Biomarkers; Neurofilament light chain (NfL); Cerebrospinal fluid biomarkers; Magnetic resonance imaging (MRI); Early diagnosis; Spinal stenosis; Diagnostic imaging.
Introduction
Spinal degeneration is influenced by multiple factors consisting of biological, physical/mechanical, and environmental factors1,2,3. Spinal degeneration encompasses several distinct conditions, including degenerative disc disease, spinal stenosis, degenerative spondylolisthesis, and degenerative cervical myelopathy1,2. However, these diseases differ in their pathological processes which makes each disease distinct due to having different clinical presentations and diagnostic features. These diseases lead to severe mobility issues, paralysis, and chronic/acute pain if/when left untreated or undiagnosed1,4. Spinal degeneration is often diagnosed after structural changes have become detectable. Diagnosis commonly relies on imaging modalities such as radiography, magnetic resonance imaging (MRI), and computed tomography (CT), which identify structural abnormalities within the spine. Consequently, the diagnosis of spinal degeneration is usually done very late in the process, but early symptoms such as back or neck pain, reduced flexibility, and radiating pain may indicate the early stages of spinal degeneration. Early detection is important and biomarkers may offer a promising diagnostic approach to this problem. Biomarkers may help identify individuals at increased risk of developing disease. The use of biomarkers may improve the detection of spinal degeneration by revealing biological changes associated with disease onset. Biomarkers may provide measurable indicators of biological changes associated with spinal degeneration. Although some biomarkers have shown associations with factors such as neuronal injury and disease severity, more research is needed to determine whether they can reliably identify signs of spinal degeneration before the occurrence of clinical symptoms or structural abnormalities5,6. Each of these methods has potential value for detecting spinal degeneration, but each also has important limitations. Additionally, electrophysiological tests may help assess neurological dysfunction in patients with spinal degeneration but cannot independently detect disease onset. This literature review aims to critically examine the existing evidence on the role of early clinical warning signs, injury-related risk factors, and biomarkers in predicting the onset of spinal degeneration. By synthesizing the findings from the latest evidence in the literature, this review will highlight the strengths and limitations of these diagnostic methods and explore their potential in improving early detection and intervention strategies for spinal degeneration. Previous studies have generally evaluated clinical findings, imaging, mechanical risk factors, and biomarkers separately. This review brings these evidence streams together while distinguishing markers of established disease from approaches with genuine potential for early detection. This distinction may help clarify which methods currently have clinical utility and which require prospective validation.
For the purposes of this review, spinal degeneration refers to degenerative disc disease, degenerative spinal stenosis, degenerative spondylolisthesis, and degenerative cervical myelopathy. These conditions differ in their pathology and clinical presentation; therefore, evidence relating to each condition should be interpreted separately. Sciatica is a clinical syndrome associated with a certain spinal pathology rather than being a degenerative disease. Studies focused primarily on acute spinal trauma, vertebral deformity, or postoperative outcomes were not considered direct evidence for early detection of degenerative spinal disease.
Methods
This study is a narrative literature review that is focused on examining evidence associated with the early detection of spinal degeneration. This review primarily includes studies published within the time frame of 2015-2026 while earlier studies were only included for background purposes.
Databases Searched
Searches were conducted in databases like PubMed, Scopus, and Google Scholar within the time frame of March-June 2026. The search was mainly focused on studies that were published onwards from 2015, some earlier studies have been included as they provided background evidence. Reference lists of some key primary studies and relevant reviews have also been searched to identify additional studies. As this study was conducted as a narrative literature review rather than a systematic review, formal PRISMA screening, duplicate-count reporting, risk-of-bias assessment, and certainty-of-evidence grading were not performed.
Search Strategy
The search was centered around the following terms: “spinal degeneration,” “biomarkers,” “cerebrospinal fluid,” “early diagnosis,” “spinal osteoarthritis,” “degenerative disk disease,” “spinal stenosis,” and “spondylolisthesis.” The objective was to get studies that were focused on biomarkers being early indicators of spinal degeneration and related diseases, as well as studies investigating other factors such as imaging techniques and electrophysiological tests.
Study Design and Eligibility Criteria
To ensure the integration of relevant and high-quality studies, the following criteria were applied: 1) Peer-reviewed studies published in English. 2) Studies focusing on the use of biomarkers, imaging techniques (e.g., X-rays, MRIs, CT Scans), or electrophysiological tests in diagnosing spinal degeneration. 3) Studies that examine biomarkers in relation to early biochemical changes within the central nervous system, specifically CSF biomarkers. 4) Clinical studies involving patients with spinal degenerative diseases or individuals at risk. 5) Studies published between 2015-2026, earlier studies were included for background purposes.
Exclusion Criteria Included: 1) Non-peer reviewed articles. 2) Studies not written in English. 3) Studies not related to spinal degeneration and biomarkers.
Data Extraction
Data were manually extracted from eligible studies, including the following key information: 1) Study design (e.g., systematic literature reviews, original research, cohort, case-control). 2) Participant demographics (age, sex, disease stage, etc.). 3) Diagnostic methods used (e.g., imaging, biomarker analysis, electrophysiological tests). 4) Type of biomarkers analyzed (e.g., CSF biomarkers, blood, urine). 5) Reported outcomes related to the diagnosis of spinal degeneration (e.g., early detection markers, biochemical changes, symptom progression).
With differences being present in study designs, patient populations, biomarkers, and diagnostic methods, the findings were synthesized narratively. The studies were organized and discussed in accordance with clinical symptoms, mechanical risk factors, imaging techniques, and biomarkers.
Results
Early Warning Signs of Spinal Degeneration
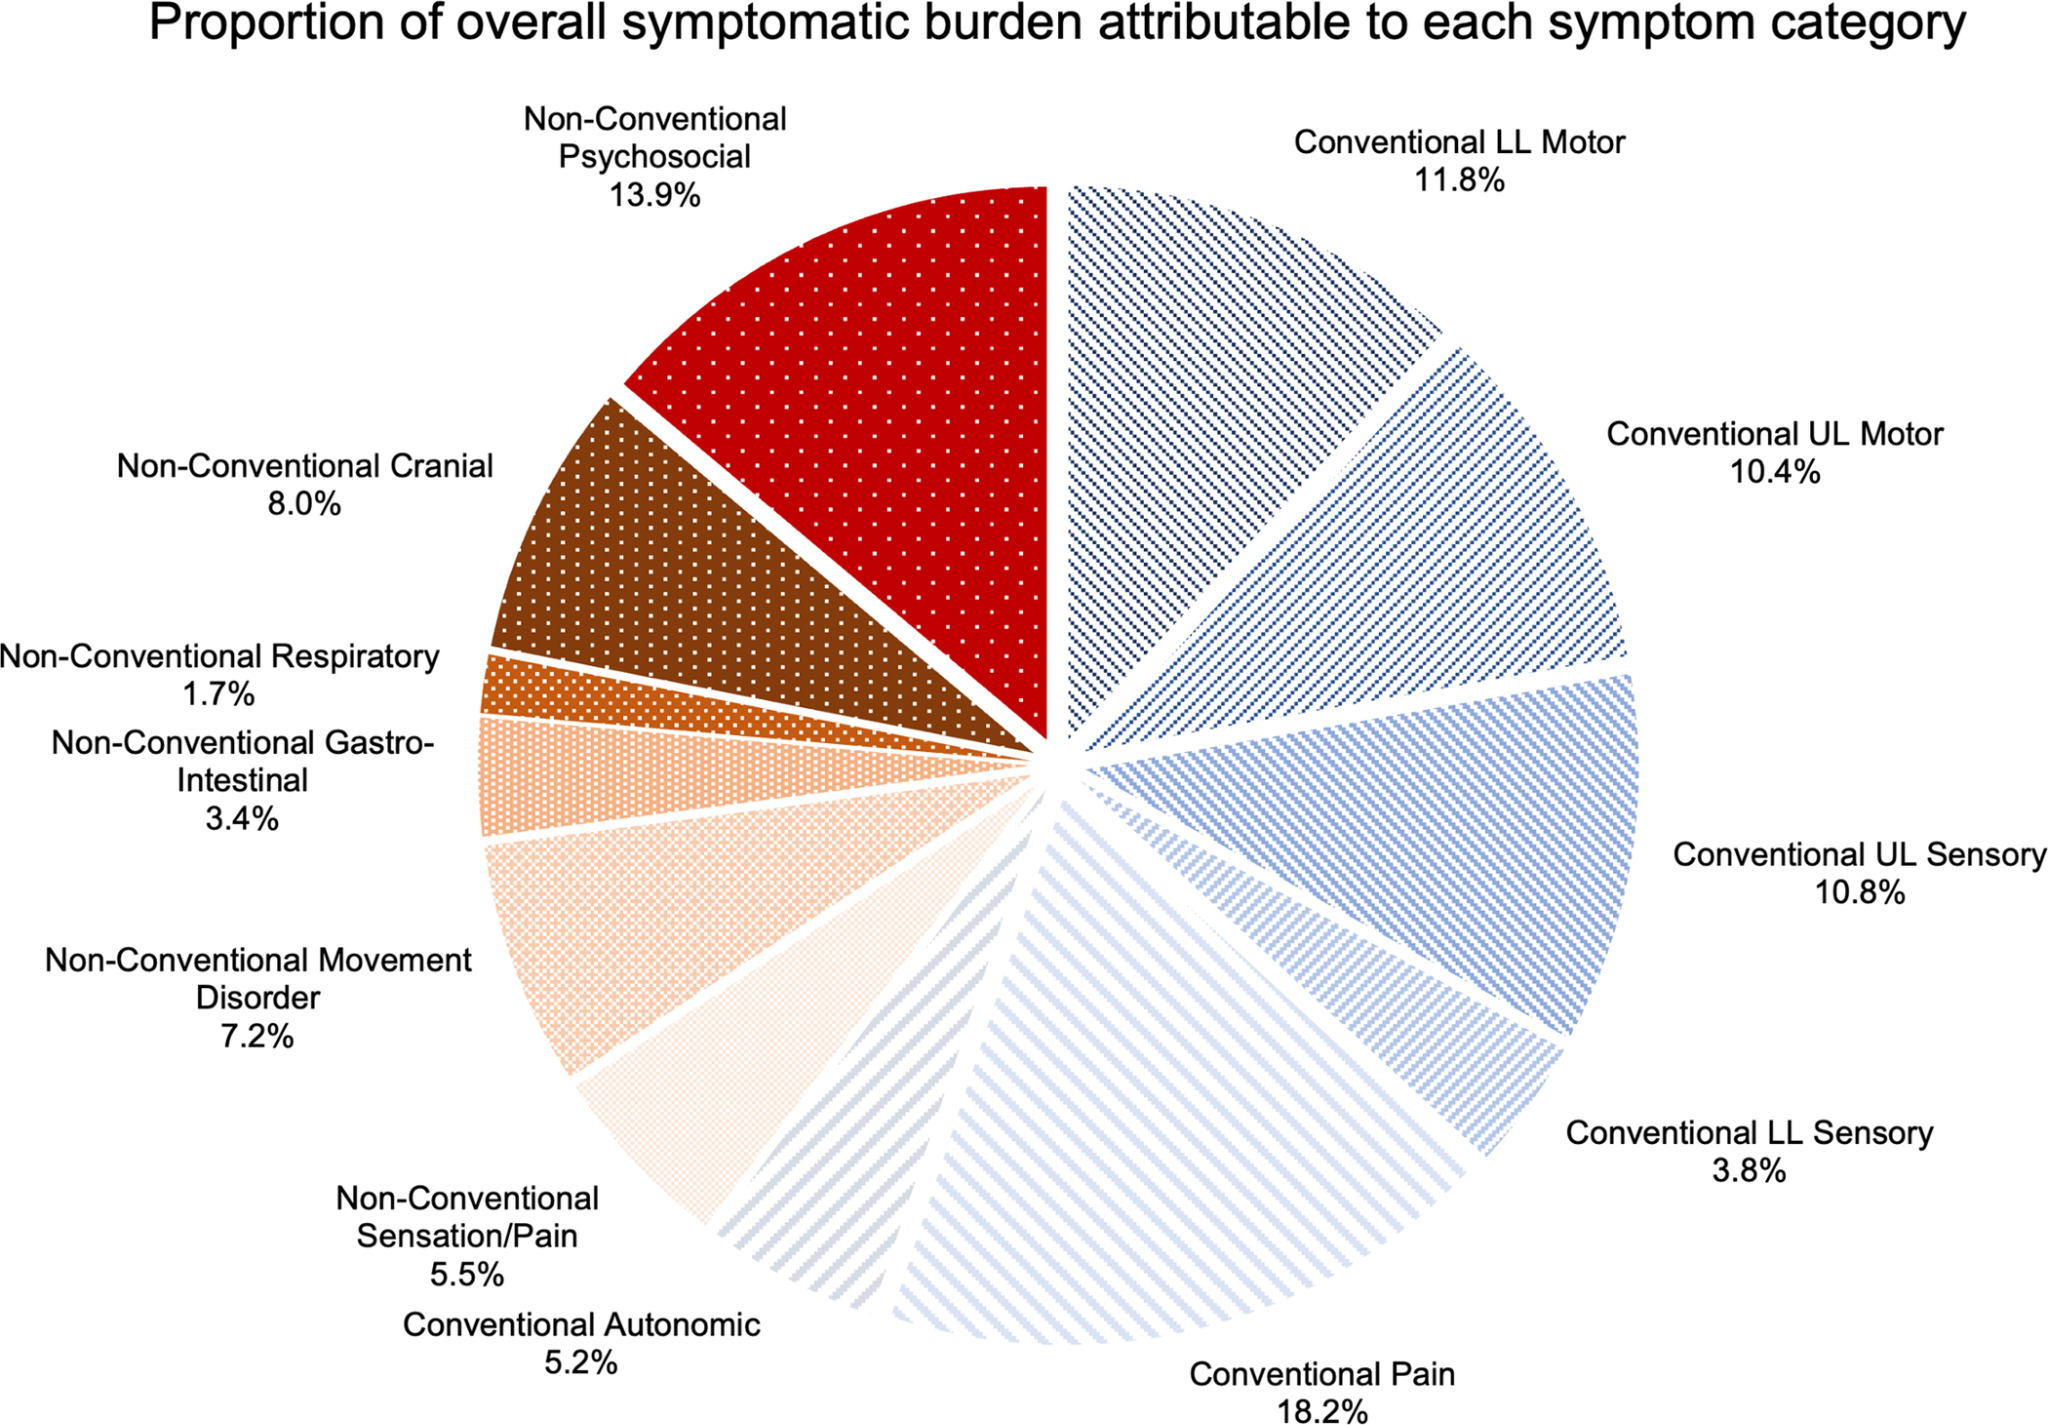
Symptoms such as back pain, reduced mobility, and sharp or pinching sensations in the back can be associated with spinal degeneration1,4. Many of these symptoms are common in adults and older individuals and may be mistaken for sprains, strains, or overuse1,4. Importantly, changes in sensation and motor function may also prompt further assessment for spinal degeneration. Degenerative cervical myelopathy (DCM) is a progressive spinal disorder of the neck’s spinal canal. In an internet survey of 171 individuals from an online degenerative cervical myelopathy (DCM) community, Munro et al. examined both current symptoms and symptoms reported at disease onset. Poor balance was the most commonly reported current symptom (84.2%), while neck pain was the most commonly reported initial symptom in 13.5% of respondents. Heavy legs was the one initial symptom associated with an early diagnosis1. The proportion of all reported symptoms attributable to each symptom group is shown in Figure 1. Conventional symptoms accounted for the majority of reported symptom burden. Together, these findings suggest that although early clinical symptoms may alert clinicians to possible spinal degeneration, symptom-based diagnosis alone lacks sufficient specificity and should be interpreted alongside additional diagnostic methods. More recent prospective studies provide stronger evidence regarding which clinical and functional findings may help distinguish degenerative cervical myelopathy from healthy status. Soufi et al. prospectively compared 139 patients with DCM and 108 age-matched healthy participants and found that neck pain, upper-extremity numbness, hand clumsiness, walking imbalance, and upper-extremity weakness had measurable diagnostic utility, although no single symptom was sufficient for diagnosis7. Quantitative functional assessment may add further objective information. Kalsi-Ryan et al. demonstrated measurable gait abnormalities in DCM using quantitative gait assessment8, while a subsequent prospective cohort study by Soufi et al. found impairments in tandem gait, single-leg stance, walking velocity, gait stability, and gait variability; importantly, some gait abnormalities were detectable even in patients who reported subjectively normal balance9. These findings support the use of structured clinical and functional testing as an adjunct to, rather than a replacement for, imaging and neurological assessment.
Injury-Related and Mechanical Risk Factors
Following the identification of early clinical symptoms, understanding the mechanisms that initiate spinal degeneration provides further insight into how disease develops, as several factors may accelerate its progression. Mechanical studies demonstrate that endplate damage significantly alters load distribution within the intervertebral disc, reducing nucleus pulposus pressure and increasing stress on the annulus fibrosus2. Repetitive loading further decompressed the nucleus and intensified stress concentrations in the anulus, especially in simulated lordotic postures. Increased stress and loading in specific regions of the spine contribute to progressive intervertebral disc degeneration and structural weakening. Repetitive loading increased pressure on the vertebral endplate, negatively affecting the nucleus pulposus and annulus fibrosus. A newly developed injury-risk model showed that cumulative axial loading significantly increases the lifetime risk of lumbar spine injury, particularly in high-exposure occupational settings3. There was a 38% risk for a high-speed planing craft operator, consistent with epidemiological evidence. These findings highlight the role of repetitive mechanical stress as a key contributor to the initiation and progression of spinal degeneration. Longitudinal population evidence also supports the importance of distinguishing risk and progression from diagnosis. In the Wakayama Spine Study, Teraguchi et al. followed 617 participants for more than four years using lumbar MRI to examine the incidence and progression of intervertebral disc degeneration and associated risk factors10. Such longitudinal studies are particularly valuable because they assess degenerative change over time rather than relying only on cross-sectional associations in patients with established disease.
Imaging-Based Detection of Spinal Degeneration
After degenerative changes occur, imaging techniques are primarily used to identify structural aberrations within the spine and confirm disease progression.
Directly correlating evidence focused on degenerative spinal disease has been found from relevant MRI studies. In cervical myelopathy, diffusion tensor imaging (DTI) has been evaluated for detecting spinal cord changes in symptomatic patients, including work by Nukala et al.11. Diffusion kurtosis imaging has also demonstrated microstructural differences between patients with DCM and healthy controls and correlations with neurological severity measures12. Additional primary studies have assessed diffusion kurtosis imaging, DTI, and magnetization-transfer MRI as quantitative approaches for characterizing spinal cord microstructural abnormalities in cervical spondylotic myelopathy13,14,15,16. Together shown, these studies denote how advanced MRI scans can detect small changes in spinal tissues that regular MRI scans could miss. However, it has not yet been proven whether these techniques will be able to detect spinal degeneration before symptoms.
Researchers have also been able to study if MRIs prove useful in evaluating and detecting intervertebral disc degeneration and lumbar spinal stenosis. Paul et al. reported that T1rho and T2 mapping detected early disc-matrix changes in an experimental model, with T1rho showing particularly strong relationships with biomechanical, histological, and glycosaminoglycan changes17. Human studies have evaluated glycosaminoglycan chemical-exchange saturation transfer and T1rho imaging in lumbar disc degeneration18, compositional MRI in patients with early or mild degenerative changes19, and MRI-based radiomics models for lumbar intervertebral disc degeneration20. In lumbar spinal stenosis, quantitative contrast-enhanced MRI has been studied for canal stenosis measurement21, while the NORDSTEN cohort showed that severe MRI abnormalities were common but were only weakly related to patient-reported disability and pain22. T2-mapping of the ligamentum flavum has also been examined as a quantitative marker of tissue alteration in lumbar spinal stenosis23. This enables support for the basis that advanced MRI can detect small changes within spinal tissues, but the amount of damage shown on scans cannot always match a patient’s severity of symptoms.
Cerebrospinal Fluid Dynamics
The patients with lumbar spinal stenosis (LSS) showed significantly attenuated levels of CSF velocity as compared to the healthy controls, and the maximum CSF velocity tended to be lower in the patients with LSS5. Reduced CSF flow velocity observed in patients with LSS suggests altered CSF dynamics associated with disease progression.
Cerebrospinal Fluid Biomarkers
Because imaging primarily detects structural changes after disease progression, researchers have increasingly investigated biomarkers capable of identifying earlier biochemical changes that could indicate a worsening spinal degeneration. The study included 20 patients with symptomatic cervical spondylotic myelopathy and 63 controls. Higher CSF concentrations of neurofilament light chain (NfL) and glial fibrillary acidic protein (GFAP) were observed in the cervical spondylotic myelopathy (CSM) group.6. CSF concentrations of NfL and GFAP were significantly elevated in patients with cervical spondylotic myelopathy, indicating neuronal or glial injury. However, the clinical utility of CSF biomarkers is limited by the invasive nature of sample collection. These findings suggest that structural proteins present in CSF may serve as useful biomarkers for assessing neuronal injury in cervical spondylotic myelopathy.
Blood-Based Biomarkers
Although CSF biomarkers provide valuable information regarding neuronal injury, their invasive collection has increased interest in blood-based biomarkers as a less invasive diagnostic alternative. In a study that involved 25 patients with established CSM and demonstrated an association between NCAM levels and disease severity, Akshota et al., found that the clinical severity of CSM on the Nurick and modified Japanese Orthopedic Association (mJOA) scales was inversely related to neural cell adhesion molecule (NCAM) levels (r=-0.529, P=0.007; r=-0.519, P=0.001, respectively)24. The Nurick scale classifies myelopathy levels on a 6-grade scale where the lowest is least severe and highest is most severe, whereas the mJOA scale being from 0-18 points is more severe in the lower ranking and less severe in the higher ranking. Akshota et al. demonstrated a significant inverse correlation between NCAM levels and clinical severity24. Thus, the findings support NCAM as a disease-associated biomarker but do not establish its ability to detect CSM before diagnosis. In a clinical study of 83 patients that were undergoing spinal surgery which was conducted by Coquelet et al., plasma levels of NfL were significantly elevated in patients with myelopathy and spinal stenosis25. NfL is a structural neuronal protein that can be released into the blood and cerebrospinal fluid following neuronal damage. Elevated plasma NfL levels were associated with increased likelihood of myelopathy and spinal stenosis. Because these patients already had clinically established spinal conditions requiring surgery, the association with elevated plasma NfL does not demonstrate early diagnosis. Given the heterogeneity of the diagnostic methods and study designs identified in the literature, a summary of the key findings, strengths, and limitations of the included studies is presented in Table 1.
Recent studies have broadened blood-based biomarker investigation beyond single structural proteins. Zheng et al. identified peripheral-blood RNA signatures that differentiated DCM from comparison groups and developed multigene models associated with diagnosis and lesion severity26. Vedantam et al. prospectively profiled serum neuronal and inflammatory proteins in patients with DCM and healthy controls, supporting the potential value of serum protein panels while also highlighting the need for larger validation cohorts27. In intervertebral disc degeneration, Rodrigues et al. found that interleukin-6 and cathepsin B were not sufficiently disease-specific as circulating biomarkers, whereas serum hyaluronic acid showed a more disease-specific association in their cohort28. More recently, Dube et al. used paired disc tissue and plasma proteomics and identified degeneration-associated extracellular-matrix changes in disc tissue but did not establish a robust plasma biomarker signature29. Together, these studies reinforce that blood biomarkers remain promising but heterogeneous, and that candidate signals require prospective validation before they can be considered reliable tools for detecting disease before clinical diagnosis.
| Study | Study design / sample | Condition | Method / biomarker | Key finding | Main limitation |
| Munro (2023)1 | Internet survey; 171 individuals from an online DCM community | Established DCM | Symptom survey | Poor balance was the most common current symptom; neck pain was the most common initial symptom (13.5%); heavy legs was associated with earlier diagnosis | Self-reported retrospective survey; symptom prevalence does not establish diagnostic accuracy |
| Adams (2000)2 | Experimental biomechanical model | Intervertebral disc degeneration | Mechanical loading / endplate injury | Endplate damage and repetitive loading altered disc mechanics and promoted degenerative changes | Experimental model; limited direct clinical applicability |
| Schmidt (2012)3 | Biomechanical injury-risk model | Lumbar spine injury risk | Cumulative axial loading | Cumulative spinal loading increased estimated lifetime injury risk | Occupational modelling; injury risk is not equivalent to degenerative disease diagnosis |
| Cook (2009)4 | Diagnostic-accuracy study in patients with cervical dysfunction | Cervical myelopathy | Clinical examination / special tests | Clinical tests and neurological signs showed diagnostic utility | Symptomatic clinical population; limited evidence for preclinical detection |
| Kim (2021)5 | Clinical comparison of LSS patients with healthy controls | Lumbar spinal stenosis | CSF-flow analysis | CSF velocity was reduced in LSS and associated with disease characteristics | Physiological rather than molecular marker; established disease and invasive assessment |
| Tsitsopoulos (2021)6 | Case-control study; 20 symptomatic CSM patients and 63 controls | Symptomatic CSM | CSF NfL and GFAP | NfL and GFAP were elevated, indicating axonal and glial injury | Established symptomatic disease; does not demonstrate preclinical detection |
| Soufi (2025)7 | Prospective diagnostic study; 139 DCM patients and 108 age-matched controls | Established DCM | Symptoms and clinical signs | Several findings had measurable diagnostic utility, but no single finding was sufficient | Assesses discrimination in established disease rather than prediction before onset |
| Kalsi-Ryan (2020)8 | Prospective clinical gait study | Established DCM | Quantitative gait assessment | Objective gait characteristics differed in DCM | Functional impairment is not disease-specific |
| Soufi (2026)9 | Prospective cohort study | DCM | Quantitative gait and balance assessment | Tandem gait and quantitative walking measures detected subtle impairment | Requires validation for screening undiagnosed populations |
| Teraguchi (2017)10 | Longitudinal population cohort; 617 participants followed >4 years | Lumbar disc degeneration | Serial lumbar MRI | Assessed incidence, progression, and associated risk factors over time | MRI-defined progression does not necessarily establish symptomatic disease |
| Nukala (2019)11 | Clinical imaging study | Symptomatic cervical spondylotic myelopathy | Diffusion tensor MRI | DTI detected spinal cord microstructural abnormalities | Established symptomatic disease; limited evidence for preclinical detection |
| Liu (2020)12 | Cross-sectional imaging study with DCM and healthy controls | Diagnosed DCM | Diffusion kurtosis MRI | DKI parameters differed from controls and correlated with neurological severity | Cross-sectional evidence in established disease |
| Yu (2020)13 | Clinical feasibility imaging study | CSM | Diffusion kurtosis MRI | DKI demonstrated measurable spinal cord microstructural abnormalities | Characterizes established disease rather than prospective early detection |
| d’Avanzo (2020)14 | Clinical quantitative imaging study | DCM | Diffusion tensor MRI | DTI measures were associated with clinical characteristics | Established disease; does not establish preclinical diagnosis |
| Suleiman (2018)15 | Clinical imaging study | CSM | Magnetization-transfer MRI | High-resolution imaging identified spinal cord tissue abnormalities | Clinical disease cohort; screening utility requires validation |
| Cloney (2018)16 | Clinical quantitative imaging study | CSM | Quantitative magnetization-transfer MRI | Anterior spinal cord measurements were associated with clinical outcomes | Association with established disease/outcomes rather than disease prediction |
| Paul (2018)17 | Experimental quantitative MRI study | Early disc degeneration model | T1rho, T2 and ADC MRI | T1rho correlated strongly with biomechanical, histological, and matrix changes | Experimental model; clinical translation requires validation |
| Togao (2018)18 | Human quantitative imaging study | Lumbar disc degeneration | GagCEST, T1rho and conventional grading | Quantitative MRI measures were associated with compositional degeneration | Cross-sectional association; predictive value remains uncertain |
| Wollschläger (2021)19 | Preliminary clinical compositional-MRI study | Early/mild lumbar disc degeneration | Chemical-exchange saturation-transfer MRI | Compositional differences associated with disc degeneration were detected | Selected population and preliminary design limit generalizability |
| Chen (2026)20 | Diagnostic modelling study | Lumbar disc degeneration | MRI-based radiomics | Radiomics models were developed for detection/classification | Requires external prospective validation |
| Jin (2020)21 | Clinical quantitative imaging study | Lumbar spinal stenosis | Contrast-enhanced quantitative MRI | Quantitative MRI was used to assess canal stenosis | Evaluates structural stenosis in established disease |
| Aaen (2022)22 | NORDSTEN clinical cohort | Established lumbar spinal stenosis | Conventional MRI | Severe MRI abnormalities showed weak relationships with disability and pain | Established/surgical population; imaging severity may not reflect symptoms |
| Takaoka (2024)23 | Clinical quantitative imaging study | Lumbar spinal stenosis | Ligamentum flavum T2 mapping | T2 mapping demonstrated tissue alterations associated with LSS | Early diagnostic performance remains uncertain |
| Akshota (2020)24 | Cross-sectional biomarker study; 25 CSM patients | Established CSM | Serum NCAM | Lower NCAM levels correlated with greater disease severity | Small cohort; severity association does not demonstrate early diagnosis |
| Coquelet (2025)25 | Clinical biomarker study; 83 surgical patients | Myelopathy / spinal stenosis | Plasma NfL and biomarker profiling | Plasma NfL was associated with spinal pathology | Established disease requiring surgery; not an early-detection cohort |
| Zheng (2025)26 | Peripheral-blood molecular biomarker study | DCM | Blood RNA signatures | Multigene signatures were associated with diagnosis and lesion severity | Small cohort; external prospective validation required |
| Vedantam (2025)27 | Prospective serum biomarker study with DCM patients and healthy controls | Established DCM | Serum neuronal/inflammatory proteins | Serum protein panels showed diagnostic/prognostic potential | Small established-disease cohort; preclinical validation required |
| Rodrigues (2019)28 | Clinical serum biomarker study | Intervertebral disc degeneration | IL-6, cathepsin B, hyaluronic acid | IL-6/cathepsin B lacked specificity; hyaluronic acid showed a stronger disease association | Limited cohort; independent validation required |
| Dube (2025)29 | Cross-sectional tissue/plasma proteomics study | Intervertebral disc degeneration | Disc tissue and plasma proteomics | Disc tissue showed degeneration-associated matrix changes without a robust plasma signature | Cross-sectional; plasma biomarker translation remains uncertain |
Abbreviations: DCM, degenerative cervical myelopathy; CSM, cervical spondylotic myelopathy; LSS, lumbar spinal stenosis; CSF, cerebrospinal fluid; NfL, neurofilament light chain; GFAP, glial fibrillary acidic protein; NCAM, neural cell adhesion molecule; DTI, diffusion tensor imaging; DKI, diffusion kurtosis imaging.
Discussion
This literature review has examined evidence supporting the use of clinical symptoms, mechanical risk factors, imaging techniques, and biomarkers in the early detection of spinal degeneration. These findings, together, show that no single diagnostic technique is not substantial enough to identify an early onset of spinal degeneration. Each method serves as a complement to each other regarding onset, progression, and severity.
Clinical symptoms are an important component of early detection as they often represent the first indication that biological changes may be occurring within the spine. Clinical symptoms can provide an early indication of DCM (degenerative cervical myelopathy). However, the prevalence in symptom(s) should not be taken as evidence of diagnostic accuracy. In the Munro et al. survey, the commonly reported symptoms were not exactly the symptoms first experienced by patients and only heavy legs was among the initial symptoms that was associated with an earlier diagnosis. These symptoms were limited by their lack of precision, as similar symptoms may also be present in a wide range of musculoskeletal and neurological conditions. Also, symptom-based assessment alone cannot provide a reliable early diagnosis.
Candid studies strengthen this interpretation by showing that clinical assessment is dependent on the type of measure used. Symptom-frequency data from Munro et al. proved useful for being able to understand certain patterns in presentation, while Soufi et al. evaluated diagnostic differences and provided substantiate evidence for specific symptoms and examination findings1,7. Similarly, quantitative gait studies suggest that objective motor measures may identify subtle functional impairment that patients do not yet perceive themselves 8,9. The present evidence supports moving from simplistic symptom prevalence to more nuanced approaches of history, neurological examination, and quantitative functional testing.
Mechanical and injury-related risk factors have also appeared to play an important role in the development and progression of spinal degeneration. Experimental studies have shown that repetitive loading, endplate damage, and cumulative spinal stress can increase degenerative changes within intervertebral discs and nearby structures. These findings corroborate the concept of how factors like occupational exposure, repetitive physical activities, and chronic mechanical stress may contribute to disease progression.
Imaging techniques still are central to the clinical evaluation of spinal degeneration, but they detect structural changes that occur after degenerative actions. This makes imaging a more effective approach for confirming disease and severity than identifying degenerative onset.
The studies have also appeared to differ in the imaging techniques that they use and the patient groups they examine. Diffusion-based MRI studies in DCM characterize spinal cord microstructural abnormalities11,12,13,14. Magnetization-transfer MRI studies provide additional evidence of tissue-level changes in patients with cervical spondylotic myelopathy15,16. In contrast, quantitative compositional MRI methods in disc degeneration are designed to detect biochemical or matrix alterations that may precede more obvious morphological changes17,18,19,20. The NORDSTEN findings demonstrate that marked structural abnormalities on routine MRI may correlate poorly with symptom severity in lumbar spinal stenosis22. Despite newer imaging techniques being able to detect any changes in tissue, these findings still have a chance of not always helping doctors in identifying the disease accurately or understanding how it affects patients. More research regarding people without symptoms or those at risk is required to precisely determine how useful these methods are for early detection.
Biomarkers can help researchers into better understanding the biological changes that are involved in spinal degeneration. Biomarkers such as NfL, GFAP, and NCAM have been able to demonstrate associations with neuronal injury and disease severity in several degenerative spinal disorders. The current evidence does not establish their ability to detect spinal degeneration before any symptoms or structural changes occur. Specifically, NfL can be promising for its elevated levels being present in both CSF and blood, this enables a less invasive method for assessing neurological damage. However, several problems still limit their use in everyday clinical practice.The problems consist of different patients, limited disease precision, and lack of standardized diagnostic limits, and the need for larger, diverse populations. Biomarkers may be still useful when considered alongside a patient’s symptoms, clinical examination, and imaging findings.
The biomarker literature presents a similar pattern. Studies of CSF NfL and GFAP, serum NCAM, and plasma biomarker signatures demonstrate molecular associations in patients with established spinal disorders6,24,25. Additional studies have investigated blood RNA, serum proteins, inflammatory markers, and tissue or plasma proteomic profiles, with variable results26,27,28,29. These findings do not establish that any of these markers can detect preclinical spinal degeneration. Moreover, negative or non-specific findings, such as the limited specificity of circulating interleukin-6 and cathepsin B and the absence of a robust plasma proteomic signature in the Dube study, are important because they show that biological plausibility does not guarantee clinical diagnostic usefulness28,29. Future studies should follow patients over time, including before when they are diagnosed, in order to better understand how biomarker levels change. Researchers also need to be able to establish clear diagnostic limits, test their findings in other patient groups, and compare biomarker results with clinical examinations and imaging findings.
One limitation of the existing research is that many studies examine individual conditions, like degenerative cervical myelopathy, cervical spondylotic myelopathy, or lumbar spinal stenosis, rather than spinal degeneration more broadly. This makes it difficult to determine whether one condition’s findings may be applicable to other degenerative spinal disorders. Many biomarker studies are inclusive to a small number of patients, this makes it harder to broaden results to larger populations. Future studies involving more patients and following them over time can be a better help in determining whether these biomarkers will be successful in identifying spinal degeneration before symptoms develop.
Future studies should focus on examining how well biomarker panels can work across a broad range of different types of spinal degeneration. Researchers should also investigate if using biomarkers alongside patient symptoms and imaging results will be able to help identify these degenerative conditions more closely and accurately. People at-risk over time may be of help to researchers that can utilize biomarkers to predict the disease before permanent structural damage develops. If these methods can be proved to be reliable, they could help doctors recognize earlier spinal degeneration, begin sooner treatment, and potentially improve long-term patient outcomes.
From a basis, evidence suggests that a multimodal approach that integrates clinical assessment, risk-factor correlation, imaging techniques, and biomarker analysis has potential to improve early detection, but a bigger substantiate reach is required to confirm within at-risk populations.
Conclusion
Early detection of spinal degeneration still is a clinical challenge due to structural aberrations being present post-disease progression. This literature review focuses on the factors of clinical symptoms, mechanical risk factors, imaging techniques, and biomarkers in improving diagnostic assessment. NfL, GFAP, and NCAM show promise as markers of biological changes despite their ability to identify early-on degeneration requiring further confirmation. An integrative diagnostic approach that combines clinical assessment, imaging, and biomarker analysis can be a useful and effective option for improving early detection, but there is still further validation required regarding clinical implementation.
Limitations
While biomarkers, particularly CSF biomarkers, show promise as indicators of disease-associated biological changes, their utility for detecting preclinical or very early spinal degeneration has not yet been established. CSF biomarkers, in particular, have limited routine clinical use because obtaining CSF requires an invasive and potentially painful procedure. Next, imaging techniques have demonstrated utility in detecting degenerative changes within the spine, but their impact is seen during the later stages and only subtle differences may be seen if trying to detect spinal degeneration using imaging techniques from the early stages. Mechanical risk factors vary among individuals because of differences in occupation, lifestyle, and genetic factors.
Abbreviations
| CSF | Cerebrospinal Fluid |
| DCM | Degenerative cervical myelopathy |
| MRI | Magnetic Resonance Imaging |
| NfL | Neurofilament Light Chain |
| LSS | Lumbar Spinal Stenosis |
| GFAP | Glial Fibrillary Acidic Protein |
| DXA | Dual-Energy X-ray Absorptiometry |
| CSM | Cervical Spondylotic Myelopathy |
| AUROC | Area Under the Receiver Operating Characteristic Curve |
Conflict of Interest
The author(s) declare no conflicts of interest related to this work.
References
- Munro CF, Yurac R, Moritz ZC, Fehlings MG, Rodrigues-Pinto R, Milligan J, Margetis K, Kotter MRN, Davies BM. Targeting earlier diagnosis: What symptoms come first in degenerative cervical myelopathy? PLoS One. 2023;18(3):e0281856. doi:10.1371/journal.pone.0281856. [↩] [↩] [↩] [↩] [↩] [↩] [↩] [↩]
- Adams MA, Freeman BJ, Morrison HP, Nelson IW, Dolan P. Mechanical initiation of intervertebral disc degeneration. Spine (Phila Pa 1976). 2000;25(13):1625-1636. doi:10.1097/00007632-200007010-00005. [↩] [↩] [↩] [↩]
- Schmidt AL, Paskoff G, Shender BS, Bass CR. Risk of lumbar spine injury from cyclic compressive loading. Spine. 2012;37(25):E1614-E1621. doi:10.1097/BRS.0b013e3182752a19. [↩] [↩] [↩]
- Cook C, Roman M, Stewart KM, Leithe LG, Isaacs R. Reliability and diagnostic accuracy of clinical special tests for myelopathy in patients seen for cervical dysfunction. J Orthop Sports Phys Ther. 2009;39:172-178. [↩] [↩] [↩] [↩]
- Kim HJ, Kim H, Kim YT, Sohn CH, Kim K, Kim DJ. Cerebrospinal fluid dynamics correlate with neurogenic claudication in lumbar spinal stenosis. PLoS One. 2021;16(5):e0250742. doi:10.1371/journal.pone.0250742. [↩] [↩] [↩]
- Tsitsopoulos PP, Holmström U, Blennow K, Zetterberg H, Marklund N. Cerebrospinal fluid biomarkers of glial and axonal injury in cervical spondylotic myelopathy. J Neurosurg Spine. 2021;34(4):632-641. doi:10.3171/2020.8.SPINE20965. [↩] [↩] [↩] [↩]
- Soufi K, Ortuno O, Castillo JA, et al. Assessing the diagnostic accuracy of symptoms and signs of degenerative cervical myelopathy: a prospective study. Sci Rep. 2025;15:37043. doi:10.1038/s41598-025-20928-4. [↩] [↩] [↩]
- Kalsi-Ryan S, Rienmueller AC, Riehm L, et al. Quantitative assessment of gait characteristics in degenerative cervical myelopathy: a prospective clinical study. J Clin Med. 2020;9(3):752. doi:10.3390/jcm9030752. [↩] [↩] [↩]
- Soufi K, Ortuno O, Chu T, et al. Enhanced measures to quantify gait and balance impairment in degenerative cervical myelopathy: a prospective cohort study. N Am Spine Soc J. 2026;27:100904. doi:10.1016/j.xnsj.2026.100904. [↩] [↩] [↩]
- Teraguchi M, Yoshimura N, Hashizume H, et al. Progression, incidence, and risk factors for intervertebral disc degeneration in a longitudinal population-based cohort: the Wakayama Spine Study. Osteoarthritis Cartilage. 2017;25(6):1122-1131. doi:10.1016/j.joca.2017.01.001. [↩] [↩]
- Nukala M, Abraham J, Khandige G, Shetty BK, Rao APA. Efficacy of diffusion tensor imaging in identification of degenerative cervical spondylotic myelopathy. Eur J Radiol Open. 2019;6:16-23. doi:10.1016/j.ejro.2018.08.006. [↩] [↩] [↩]
- Liu Z, Bian B, Wang G, Tian C, Lv Z, Shao Z, Li D. Evaluation of microstructural changes in spinal cord of patients with degenerative cervical myelopathy by diffusion kurtosis imaging and investigate the correlation with JOA score. BMC Neurol. 2020;20(1):185. doi:10.1186/s12883-020-01752-x. [↩] [↩] [↩]
- Yu J, Sun Y, Cao G, Zheng X, Jing Y, Li C. Diffusional kurtosis imaging in evaluation of microstructural changes of spinal cord in cervical spondylotic myelopathy: feasibility study. Medicine (Baltimore). 2020;99(46):e23300. doi:10.1097/MD.0000000000023300. [↩] [↩] [↩]
- d’Avanzo S, Ciavarro M, Pavone L, et al. The functional relevance of diffusion tensor imaging in patients with degenerative cervical myelopathy. J Clin Med. 2020;9(6):1828. doi:10.3390/jcm9061828. [↩] [↩] [↩]
- Suleiman LI, Weber KA 2nd, Rosenthal BD, et al. High-resolution magnetization transfer MRI in patients with cervical spondylotic myelopathy. J Clin Neurosci. 2018;51:57-61. doi:10.1016/j.jocn.2018.02.023. [↩] [↩] [↩]
- Cloney MB, Smith ZA, Weber KA 2nd, Parrish TB. Quantitative magnetization transfer MRI measurements of the anterior spinal cord region are associated with clinical outcomes in cervical spondylotic myelopathy. Spine. 2018;43(9):675-680. doi:10.1097/BRS.0000000000002470. [↩] [↩] [↩]
- Paul CPL, Smit TH, de Graaf M, et al. Quantitative MRI in early intervertebral disc degeneration: T1rho correlates better than T2 and ADC with biomechanics, histology and matrix content. PLoS One. 2018;13(1):e0191442. doi:10.1371/journal.pone.0191442. [↩] [↩] [↩]
- Togao O, Hiwatashi A, Wada T, et al. A qualitative and quantitative correlation study of lumbar intervertebral disc degeneration using glycosaminoglycan chemical exchange saturation transfer, Pfirrmann grade, and T1-rho. AJNR Am J Neuroradiol. 2018;39(6):1369-1375. doi:10.3174/ajnr.A5657. [↩] [↩] [↩]
- Wollschläger LM, Nebelung S, Schleich C, et al. Evaluating lumbar intervertebral disc degeneration on a compositional level using chemical exchange saturation transfer: preliminary results in patients with adolescent idiopathic scoliosis. Diagnostics (Basel). 2021;11(6):934. doi:10.3390/diagnostics11060934. [↩] [↩] [↩]
- Chen Y, Wang F, Yu L, Bi H, Yuan F, Luo M. Four MRI-based radiomics models for diagnosis of lumbar intervertebral disc degeneration. J Imaging Inform Med. 2026. Advance online publication. doi:10.1007/s10278-026-01966-4. [↩] [↩] [↩]
- Jin YJ. Quantification of lumbar spinal canal stenosis by quantitative fat-suppressed contrast-enhanced magnetic resonance imaging. J Clin Med. 2020;9(9):3084. doi:10.3390/jcm9103084. [↩] [↩]
- Aaen J, Austevoll IM, Hellum C, et al. Clinical and MRI findings in lumbar spinal stenosis: baseline data from the NORDSTEN study. Eur Spine J. 2022;31(5):1391-1398. doi:10.1007/s00586-021-07051-4. [↩] [↩] [↩]
- Takaoka H, Eguchi Y, Koroki J, et al. Quantitative evaluation of the lumbar ligamentum flavum using MRI T2-mapping: efficacy of its clinical application in patients with lumbar spinal stenosis. J Orthop Sci. 2024;29(1):101-108. doi:10.1016/j.jos.2022.12.013. [↩] [↩]
- Akshota N, Friedlander A, Hershkovich O, Gurevich M, Givon U, Sakhini M, Achiron A. Neural cell adhesion molecule (NCAM), a serum biomarker indicative for the severity of cervical spondylotic myelopathy. Clin Spine Surg. 2020;33(4):E178-E184. doi:10.1097/BSD.0000000000000952. [↩] [↩] [↩] [↩]
- Coquelet P, Da Cal S, El Hage G, et al. Specific plasma biomarker signatures associated with patients undergoing surgery for back pain. Spine J. 2025;25(1):32-44. doi:10.1016/j.spinee.2024.09.002. [↩] [↩] [↩]
- Zheng Z, Chen J, Xu J, Jiang B, Li L, Li Y, Dai Y, Wang B. Peripheral blood RNA biomarkers can predict lesion severity in degenerative cervical myelopathy. Neural Regen Res. 2025;20(5):1764-1775. doi:10.4103/NRR.NRR-D-23-01069. [↩] [↩] [↩]
- Vedantam A, Rahman M, Salam S, Banerjee A, Satkunendrarajah K, Budde MD, Meier TB. Serum protein biomarkers for degenerative cervical myelopathy: a prospective study. J Neurosurg Spine. 2025;42(5):718-726. doi:10.3171/2025.1.SPINE241085. [↩] [↩] [↩]
- Rodrigues LMR, Oliveira LZ, Silva MBRD, Accardo CM, Giglio ABD, Pinhal MADS. Inflammatory biomarkers in sera of patients with intervertebral disc degeneration. Einstein (Sao Paulo). 2019;17(4):eAO4637. doi:10.31744/einstein_journal/2019AO4637. [↩] [↩] [↩] [↩]
- Dube CT, Gilbert HTJ, Rabbitte N, et al. Proteomic profiling of human plasma and intervertebral disc tissue reveals matrisomal, but not plasma, biomarkers of disc degeneration. Arthritis Res Ther. 2025;27(1):28. doi:10.1186/s13075-025-03489-9. [↩] [↩] [↩] [↩]